FACT OR FICTION FRIDAY || All rotator cuffs tears need surgery.

FACT OR FICTION FRIDAY || All rotator cuffs tears need surgery.

Answer: FICTION. The devil is in the detail!

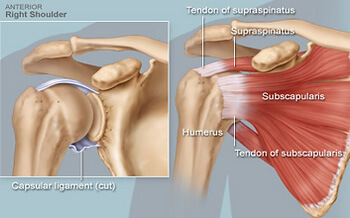
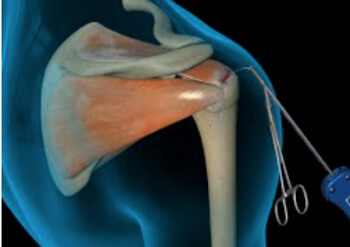
The rotator cuff is a group of 4 muscles that aid in providing stability through range for the shoulder joint, particularly overhead. There are multiple risk factors for RC tears, but most are down to overactivity of the shoulder joint decreased conditioning of the shoulder complex, which comes with age. In fact, cuff tears are common in individuals over the age of 40 with linear increase in incidence as we get older.

Pain with movement and function is one of the biggest symptoms of a rotator cuff tear. However, it is important to know that a sizeable portion of RC tears are actually asymptomatic and don’t cause the person any pain or discomfort! A study by Minagawa and Yamamoto in 2013 found that in a screening of 664 village residents, 147 subjects had RC tears on a medical imaging screening. Surprisingly 65% of them had no symptoms at all and didn’t have any shoulder complaints.

Mid Potion Achilles Tendinopathy Location

Surgery vs. Conservative Management

The two main ways of treating a cuff tear is either through conservative management with your physiotherapist or down the surgical route, which is also then followed by physiotherapy rehabilitation.

SO, back to the original question: “Do I need surgery?”. As always – it is a case by case decision!! There is no definitive evidence for supporting one over the other generally speaking!

Weighing the Risks and Benefits

However, it is vitally important to note that each option comes with their own pros and cons. Furthermore, it is important to remember that just as every person is different, each case of rotator cuff tear is different. Young vs old, acute vs degenerative RC tear, current and desired future function, pain levels, radiographic findings, previous history of shoulder trauma and the patient’s wishes are only some of the questions that aid in the decision process.

The best way to decide would be to contact us to asses you and discuss both options and what your goals of rehab are so that a tailored plan can be developed WITH you. To read more about RC tears, read our blog here

To get your shoulder back on track, book online or give us a call on (07) 3102 3337.

PREVENT | PREPARE | PERFORM

Until next time, Praxis What You Preach

📍 Clinics in Teneriffe, Buranda, and Carseldine

💪 Trusted by athletes. Backed by evidence. Here for everyone.

Related Articles

ROTATOR CUFF TEARS || Do I Need Surgery?

That age old question in which the answers seems to be becoming increasingly more difficul…

Rotator Cuff Repair: A Physiotherapy Guide on Recovery and Rehabilitation

Rotator cuff repair is a common surgery for persistent shoulder pain and dysfunction, but …

Shoulder Stabilisation and Bankart Repair: Your Path Back to Sport

Recovering from a shoulder stabilisation surgery, particularly a Bankart repair, can feel …
Stingers AKA Neural traction injuries

Stingers AKA Neural traction injuries

SUMMARY:

  • Stingers are essentially a tractioning of the neural system
  • This can cause pain, movement and sensation changes
  • Chronic traction to the nervous system can have a cumulative effect on nerve function
  • The more damage to the nerve, the more serious the outcome
  • We shouldn’t be as dismissive of “stingers”, particularly if they are recurrent
  • Physiotherapy has a role to play

STINGERS:

Stingers have been the catch cry of many contact sports over the years. Often dismissed as ‘just a stinger’, trauma to the nervous system should probably be taken a little more seriously, as we delve into detail today.

Stingers are most commonly experienced in contact sports whereby the shoulder of a players is forcefully depressed, as experienced with a tackle in NRL or union. A large range of motion over a short period of time can result in a ‘traction’ of the Brachial Plexus (a network of nerves formed from exiting branches of the spinal cord in the neck that transverse to the shoulder and arm). Thus network of nerves sends signals from your spinal cord to your shoulder, arm and hand and thereby providing feeling and movement to these regions.

BACKGROUND:

To understand a stinger injury, a clear understanding of nerves and nerve related injuries is required. A nerve is an enclosed, cable-like bundle of nerve fibres called axons, in the peripheral nervous system. A nerve provides a common pathway for the electrochemical nerve impulses that provide a number of functions, including getting our muscles to move!

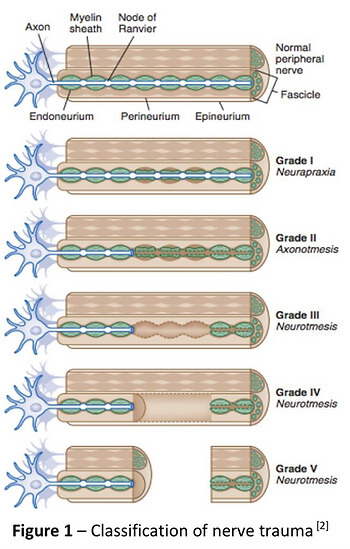
Seddon and Sunderland present a five-grade classification scale for nerve related injuries[1-4]. Figure 1 illustrates the physiological changes that occur through each grade of injury. Essentially it outlines the greater amount of disruption to the anatomy of the nerve.

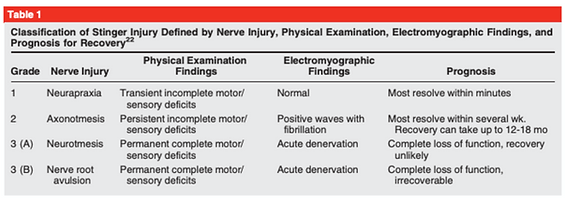
The more damage to the nerve, the more serious the outcome. Table 1 outlines the three different grades of stinger injuries.[4, 5] The most common stinger is a grade 1 injury, which represents a neurapraxia, or nerve stretch injury, without axonal disruption.[4] In an acute setting, this can result in motor and sensory loss/changes, which usually resolve within minutes.[1, 4] Grade 2 and 3 involve a higher degree of nerve injury, usually involving a crush, transection or compression mechanism.[1]

Chronic traction to the nervous system can have a cumulative effect on nerve function. This is termed “chronic stinger syndrome” and represents a distinct entity from acute stingers that may reflect long- standing structural changes of the subaxial spinal canal and chronic irritation/degeneration of the exiting nerve root complex.[4, 6]. This sounds complex but essentially means

Mid Potion Achilles Tendinopathy Location

A Clinical Example from Zac

“During a Gridiron match, a player was injured whilst making a tackle. I reviewed the player on field and he was unable to utilise his right upper limb (full paralysis) from shoulder down to his hand. The player was removed from the field immediately to be further assessed and monitored. A complete neurovascular assessment was performed, assessing motor function/strength, sensation, reflexes, and vascular status, as well was the cervical spine. Motor and sensation changes were the only deficits noted and were reviewed frequently. After roughly five minutes, the player demonstrated full upper limb motor strength and sensation, with nil lingering symptoms. In collaboration with the patient, it was decided he would return to match play immediately. The patient was monitored throughout the game and reported no further symptoms.”

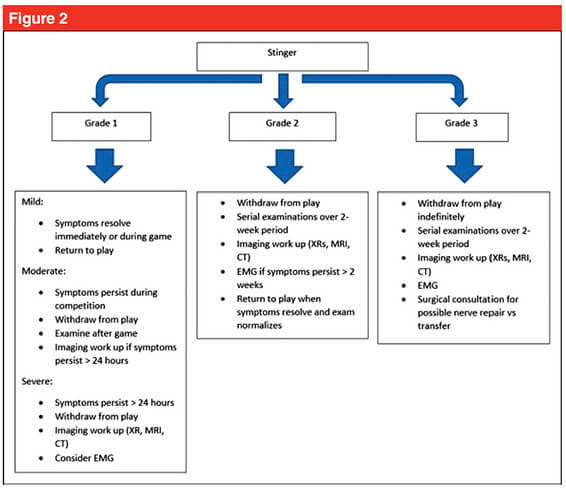
Figure 2 shows a proposed decision tree when managing stinger injuries.[4] This clinical example outline above fits the Grade 1 Mild category as he was able to return to competition with nil lingering symptoms. Despite the lack of symptoms during the game, it is recommended the patient be reviewed again both after the game and weekly for two weeks to ensure a full resolution of symptoms.[4, 7]

Photo from the Praxis Physiotherapy article: Stingers AKA Neural traction injuries

The role for neural mobilisation?

Current non-surgical management involves rest, pain control and resistance training[4]. Though not explored within the literature, neural mobilization may have an important role in patients with persistent symptoms, such as Grade 1 moderate to severe, and more recurrent neuropraxias. Though not assessed in this specific population, there is evidence for neural tissue management being superior to minimal intervention for pain relief and reduction of disability in nerve related chronic musculoskeletal pain.[8] It is biologically plausible that recurrent neuropraxias may respond in a similar way, utilising neural mobilisation (tensioning or sliding) and mobilisation of surrounding structures.

Management of persistent Grade 1 injuries may differ slightly, specifically if the suspected mechanism of injury was through traction rather than compression. The nerve structures may have a heightened sensitivity to tensioning based techniques due to the similar mechanism of injury and may respond better acutely to sliding techniques which limit the strain on the nerve and focus on excursion. Tensioning techniques may be important in the sub-acute phase by loading the patient’s nervous system (i.e. increased strain) in preparation for return to function (i.e. tackling with acute traction on the brachial plexus).

In summary, perhaps we shouldn’t be as dismissive of “stingers”, particularly if they are recurrent for you! If you have any questions or would like to see one of our physios regarding your injury, feel free to contact us on (07) 3102 3337 or book online on our website

Prevent | Prepare | Perform

Until next time, Praxis What You Preach

📍 Clinics in Teneriffe, Buranda, and Carseldine

💪 Trusted by athletes. Backed by evidence. Here for everyone.
REFERENCES:

Menorca, R.M.G., T.S. Fussell, and J.C. Elfar, Nerve physiology: mechanisms of injury and recovery. Hand clinics, 2013. 29(3): p. 317-330.

Tsao B, B.N., Bethoux F, Murray B, Trauma of the Nervous System, Peripheral Nerve Trauma. 6th ed. In: Daroff: Bradley’s Neurology in Clinical Practice. 2012.

Sunderland, S., A classification of peripheral nerve injuries producing loss of function. Brain, 1951. 74(4): p. 491-516.

Ahearn, B.M., H.M. Starr, and J.G. Seiler, Traumatic Brachial Plexopathy in Athletes: Current Concepts for Diagnosis and Management of Stingers. J Am Acad Orthop Surg, 2019.

Feinberg, J.H., Burners and stingers. Phys Med Rehabil Clin N Am, 2000. 11(4): p. 771-84.

Presciutti, S.M., et al., Mean subaxial space available for the cord index as a novel method of measuring cervical spine geometry to predict the chronic stinger syndrome in American football players. J Neurosurg Spine, 2009. 11(3): p. 264-71.

Aldridge, J.W., et al., Nerve entrapment in athletes. Clin Sports Med, 2001. 20(1): p. 95-122.

Su, Y. and E.C. Lim, Does Evidence Support the Use of Neural Tissue Management to Reduce Pain and Disability in Nerve-related Chronic Musculoskeletal Pain?: A Systematic Review With Meta-Analysis. Clin J Pain, 2016. 32(11): p. 991-1004.

Related Articles

Pain in the Neck: Why Your Neck Hurts and What To Do About It

Neck pain is one of the most common – and frustrating – conditions we treat at Praxis Phys…

Hamstring Strain Injuries: Lessons from Personal Experience and the Latest Research

Discover why hamstring strains are so common in running athletes, including personal insig…

FACT OR FICTION – I’m in pain, I’m damaging something

FICTION! Stay with me on this one as it can be confusing. What Is Pain, Really?Pain = An u…
Shoulder Pain

Shoulder Pain

Do you have a “good” shoulder and a “bad” shoulder? Have you been putting up with that grumbly shoulder for weeks, months or even years? Shoulder pain can put a real dampener on your activity levels — but it doesn’t need to.

Shoulder pain is one of the most common reasons people see a physio, but it’s also one of the most misunderstood. That’s partly because “shoulder pain” isn’t actually a diagnosis — it’s a symptom that can come from several quite different problems, each needing a different approach. Getting the cause right is the difference between a plan that works and months of guessing.

Some of the more common complaints we hear:

  • Sharp, dull, deep, aching pain around the shoulder
  • “Popping” or “crackling” sounds or sensations in the joint
  • Pain in the mornings after lying on that side
  • A feeling of the arm “separating,” “popping out,” “slipping” or feeling unstable
  • Losing power on overhead tasks like swimming, throwing or gym work
  • Pain, pins and needles, or numbness down the arm, or pain running up into the neck
  • The shoulder feeling stiff, tight, or even “frozen”
Photo from the Praxis Physiotherapy article: Shoulder Pain

What’s Actually Causing Your Shoulder Pain?

Below are the most common causes we see in clinic. If one of these sounds like you, we’ve linked through to a deeper dive where we’ve already written about it.

Rotator Cuff & Subacromial Pain (By Far the Most Common)

This group — rotator cuff tendinopathy, impingement, tears, and bursitis — accounts for roughly two-thirds of all shoulder pain presentations. It typically shows up as pain with overhead movement, weakness reaching up or behind your back, and that classic ache lying on the affected side at night.

The good news: a rotator cuff tear on a scan doesn’t automatically mean you need surgery. Plenty of people have rotator cuff changes on imaging with zero pain — imaging alone doesn’t tell the whole story. How your shoulder actually moves and performs matters more than what a picture shows.

Read more: Rotator Cuff Repair: A Physiotherapy Guide on Recovery and Rehabilitation · Rotator Cuff Tears — Do I Need Surgery?

Shoulder Instability

If your shoulder feels like it’s “slipping,” “popping out,” or genuinely unstable — rather than just painful — this points toward instability rather than a cuff problem. It’s common after a dislocation or in people with naturally more mobile joints, and needs a different rehab emphasis: control and stability, not just strength.

Read more: Shoulder Stabilisation and Bankart Repair: Your Path Back to Sport

Throwing & Overhead Sport Injuries

Swimmers, throwers, and overhead athletes load the shoulder differently to the rest of us, and the injuries that follow — and the rehab they need — are their own category. If you’re losing power or accuracy on your throw, or pain shows up specifically loading overhead, this is usually where to look.

Read more: Throwing Injuries · From Pitch to Pressing: Leading the Way in Shoulder Pain Recovery

Frozen Shoulder (Adhesive Capsulitis)

This one’s distinct: stiffness dominates over pain. Rather than pain with specific movements, you lose range of motion in most directions — reaching behind your back or overhead becomes genuinely difficult, not just uncomfortable. It’s more common in women, typically develops between 40–70, and is linked to diabetes and thyroid conditions. It tends to run its own course over months, and the right hands-on and exercise approach can make that course far more bearable.

AC Joint Pain

The acromioclavicular (AC) joint sits at the very top of the shoulder, where the collarbone meets the shoulder blade. Pain here is usually well localised to that spot and often follows a direct knock, a fall onto the shoulder, or heavy pushing/bench-press-type loading. It’s a much more targeted, easier problem to pinpoint on assessment than the cuff-related causes above.

Referred Pain from the Neck

Sometimes the shoulder isn’t the problem at all — the neck is. Pain, pins and needles, or numbness running from the neck down into the shoulder and arm often traces back to the cervical spine rather than the shoulder joint itself. If your shoulder pain came with neck stiffness or arm symptoms, this is worth ruling in or out early.

Read more: Pain in the Neck: Why Your Neck Hurts and What To Do About It

How We Diagnose It

Because these causes overlap in how they feel, an accurate diagnosis comes from a proper physical assessment — how your shoulder moves, where it’s weak, and what specifically reproduces your pain — not from an X-ray or MRI in isolation. Imaging has its place, but current best-practice guidelines are clear that treatment decisions should be based on what your shoulder can and can’t do functionally, not just what a scan shows.

Treatment: What Actually Works

Across the current research, one finding comes up again and again: targeted, shoulder-specific exercise therapy is the strongest evidence-based treatment for shoulder pain, and it holds up as well as — or better than — injections, manual therapy alone, or jumping straight to surgery for most presentations. A well-run exercise program, tailored to what your assessment finds, can provide meaningful pain relief that lasts well beyond the treatment period itself.

That doesn’t mean hands-on treatment has no role — manual therapy alongside exercise can help in the short term, particularly for stiffness-dominant presentations like frozen shoulder. But exercise is the cornerstone, not the afterthought.

What this looks like in practice:

  • A thorough assessment to identify which of the causes above best fits your presentation
  • A program targeting the right muscles for your specific problem (cuff-focused, scapular control, or general mobility, depending on diagnosis)
  • Gradual, progressive loading — building capacity rather than just chasing pain relief
  • A realistic timeline: most people see genuine improvement within 6–12 weeks of consistent work

Sport-Specific and Injury-Specific Rehab

If you already know your specific injury or you’re working toward getting back to sport, these go deeper on rehab and return-to-play:

Get It Properly Assessed

Whether your symptoms are from wear and tear or an acute injury from sport, work, or everyday life, we’re here to help. The shoulder needs to be both strong and mobile — if yours isn’t, get in touch today on (07) 3102 3337 or book online.

📍 Clinics in Teneriffe, Buranda, and Carseldine

💪 Trusted by athletes. Backed by evidence. Here for everyone.